
Planning journeys around the nearest bathroom, carrying spare clothes, or getting up repeatedly at night to change a pad can make a period take over your week. You do not need to measure blood loss in a cup before asking for help. How the bleeding affects your daily life matters.
Heavy periods can often be treated with medicines or a hormonal intrauterine system (IUS), but the choice depends on the cause, your health and your pregnancy plans. Surgery is appropriate for some women. There is no requirement to try every tablet before discussing it.
This guide covers recognising heavy bleeding, choosing investigations, treating iron deficiency, and the main treatment options from tablets to procedures. Clinical sources reviewed 13 September 2026; original publication date retained.
When bleeding needs urgent care
If you are soaking a pad or tampon every hour for more than two hours and feel faint, dizzy, short of breath or have chest pain, seek emergency care locally. Collapse or severe weakness also needs immediate help. Do not wait to finish a bleeding diary or receive a WhatsApp reply. This follows ACOG’s advice on acute abnormal uterine bleeding.
Ongoing rapid bleeding without those symptoms still warrants prompt medical advice. If pregnancy is possible, particularly with a missed period or new pelvic pain, tell the clinician: pregnancy-related bleeding needs a different assessment. ACOG’s heavy-bleeding guidance includes miscarriage and ectopic pregnancy among possible causes of abnormal bleeding.
This article mainly concerns recurring heavy periods in women who are not pregnant. Bleeding after menopause, between periods or after sex should be discussed with a clinician rather than automatically treated as a heavy period.
What counts as heavy
Heavy menstrual bleeding, sometimes called menorrhagia, is bleeding that interferes with physical, social or emotional wellbeing. An 80 ml threshold has been used in research, but it is not a volume you must prove before receiving treatment. NICE guideline NG88 places quality of life, rather than measured blood loss alone, at the centre of care.
Practical signs described by the NHS include:
- Changing a pad or tampon every one to two hours, or emptying a menstrual cup more often than its instructions suggest.
- Bleeding for more than seven days.
- Passing clots larger than about 2.5 cm.
- Using two types of period protection together, or leaking onto clothes or bedding.
- Missing work, avoiding activities, or frequently feeling tired or breathless.
Any one concern can justify a consultation; you do not have to meet several criteria. Pad absorbency and changing habits vary, so pad counts help describe your experience rather than precisely measure blood loss.
What causes heavy periods
The cause cannot be identified from clot size or flow alone. Common possibilities in ACOG’s clinical guidance include:
- Fibroids: usually non-cancerous growths in the uterine muscle. Their position and effect on the uterine cavity matter, not just whether a scan finds one.
- Adenomyosis: tissue similar to the womb lining within the muscle wall, often associated with painful, heavy periods.
- Polyps: growths in the womb lining that may cause heavy or between-period bleeding.
- Irregular ovulation: this can occur with PCOS or during the transition towards menopause and may lead to infrequent, heavy bleeding.
- Medicines or contraception: blood thinners, aspirin and copper IUDs can contribute. Do not stop a prescribed blood thinner yourself.
- Bleeding disorders: particularly relevant when periods have been heavy from the beginning, with easy bruising, nosebleeds, excessive bleeding after procedures, or a family history.
Thyroid disease is another possibility when there are other suggestive symptoms. Less commonly, abnormal changes in the womb lining, including cancer, need to be excluded. This is why persistent irregular or between-period bleeding changes the investigation plan. Sometimes no structural cause is found, and treatment can still help; a normal scan does not mean the bleeding is unimportant.
Which tests do you need?
Start with your bleeding pattern, pain, medicines, previous treatments and pregnancy plans. Bring existing reports so tests do not have to be repeated unnecessarily. Examination and investigations are selected from that history, not ordered as the same ultrasound/ferritin/thyroid package for everyone.
Blood count and iron stores
NICE NG88 recommendation 1.2.6 recommends a full blood count for all women with heavy menstrual bleeding, alongside treatment rather than delaying treatment until every result is back. It checks for anaemia.
Ferritin measures iron stores and is a separate question from the blood count. In July 2026, NICE removed its older recommendation against routine ferritin testing, explaining that discouraging it was not justified given the risk of iron deficiency in women with heavy bleeding. Ask whether ferritin or other iron studies should be included in your assessment. NICE did not replace it with a recommendation to test every woman. Discuss iron assessment without assuming that an entire scan-and-blood-test bundle is required.
NICE’s remaining laboratory recommendations say:
- Thyroid tests are indicated when other signs or symptoms suggest thyroid disease, not automatically for heavy bleeding alone.
- Routine female-hormone panels are not part of the standard heavy-bleeding work-up.
- Clotting-disorder testing should be considered when bleeding has been heavy since periods began and personal or family history suggests a disorder.
A pregnancy test may also be needed when pregnancy is possible, as described by ACOG.
Ultrasound, hysteroscopy and a lining sample
The first investigation depends on what the clinician is looking for. NICE NG88 section 1.3 distinguishes:
| Situation | Investigation to discuss |
|---|---|
| A suspected pelvic mass, enlarged uterus or difficult/inconclusive examination | Pelvic ultrasound |
| Marked period pain or a bulky, tender uterus suggesting adenomyosis | Usually transvaginal ultrasound; discuss alternatives if unsuitable or declined |
| Persistent bleeding between periods or suspected cavity polyps/submucosal fibroids | Hysteroscopy, which looks directly inside the womb |
| Higher risk of abnormal womb-lining changes | Endometrial sampling as part of the assessment |
A scan and hysteroscopy answer different questions. Ultrasound can miss some cavity abnormalities. NICE recommends considering biopsy during hysteroscopy in higher-risk situations, including persistent irregular/intermenstrual bleeding, infrequent heavy bleeding with obesity or PCOS, tamoxifen use, or unsuccessful treatment. Your clinician should explain why a sample is needed and how it will be obtained; not everyone with heavy periods needs one.
If history and examination suggest a low risk of a structural or lining problem, NICE allows medical treatment to start without first investigating the cause. That is an assessed decision, not permission to ignore new symptoms.
If you would like help understanding reports or options already offered, message Dr. Suganya on WhatsApp. Dr. Suganya Venkat is an OB-GYN with 15+ years of experience and consults online through Fertilia. Examinations, procedures and urgent treatment need a local clinician.
Treat the iron deficiency as well as the bleeding
Iron treatment replaces what has been lost; bleeding treatment reduces ongoing loss. One does not substitute for the other. If iron deficiency or anaemia is found, your clinician can recommend replacement and follow-up blood tests. Report side effects rather than quietly stopping a prescribed supplement.
Food supports recovery, but it is not a replacement for prescribed treatment of iron-deficiency anaemia. Beans and lentils, leafy vegetables and meat if you eat it can contribute iron; in an Indian kitchen, dal, chana and greens are practical options. NHS anaemia guidance describes food alongside iron tablets and repeat testing. Tea and coffee can reduce absorption; ask how to space them around your iron medicine.
Do not assume every episode of tiredness is from iron deficiency, or that improving haemoglobin means the bleeding no longer needs attention.
Treatment options and their trade-offs
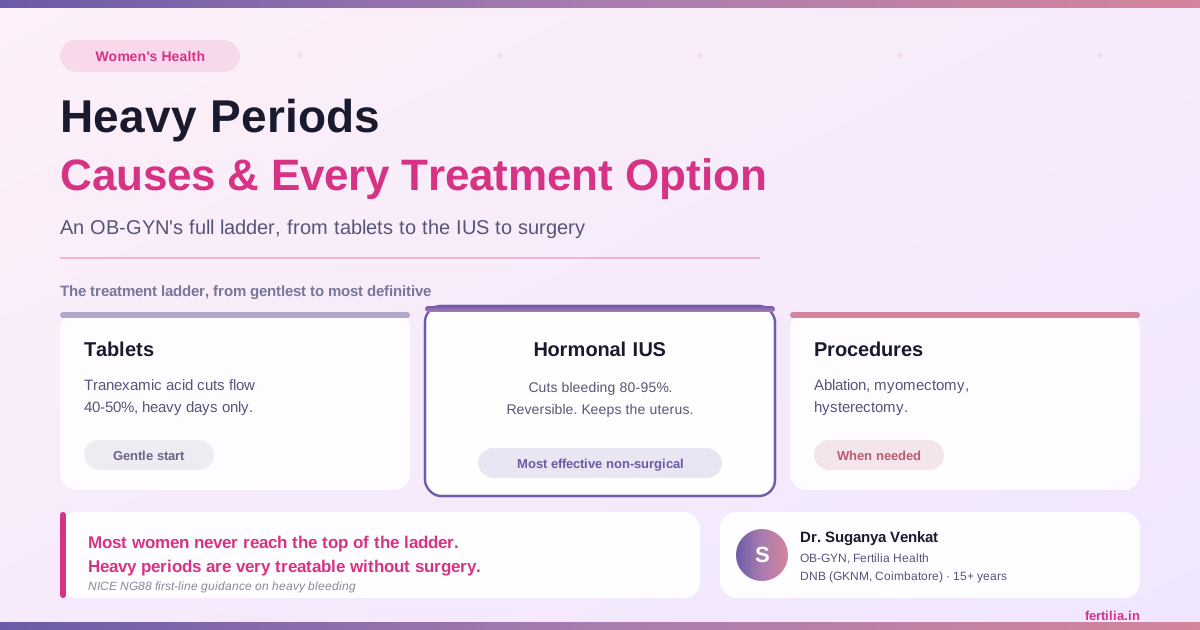
There is no fixed “gentlest-to-strongest” sequence for everyone. NICE NG88 says to consider the cause, other symptoms, medical conditions and your preferences. Medicines may be used while investigations or a procedure are being arranged.
Non-hormonal tablets
Tranexamic acid reduces bleeding and is generally used during the period as prescribed. NSAIDs, such as mefenamic acid or ibuprofen, may help both bleeding and period pain. These are recognised options in NICE NG88, including when an LNG-IUS is declined or unsuitable.
Neither is a contraceptive, but that does not mean either is suitable for everyone trying to conceive. Tell the prescriber if pregnancy is possible. NHS tranexamic-acid guidance calls for checking clot history, kidney problems and other relevant conditions. Do not add it yourself to a combined contraceptive pill: the NHS advises discussing that combination because of clot risk.
NSAIDs need particular care with stomach ulcers, kidney disease, previous reactions and interacting medicines. NHS ibuprofen guidance covers these checks. Do not combine different NSAIDs or treat a possible pregnancy-related bleed as an ordinary period. The dose and duration should come from your prescriber and the supplied Indian product, not a generic online schedule.
Hormonal tablets and contraceptive methods
Combined hormonal contraception can reduce bleeding and provide contraception. It is not suitable with some medical histories, including migraine with aura or certain clotting and cardiovascular risks; see NHS combined-pill eligibility guidance.
Cyclical oral progestogens are another treatment option. Progestogen-only contraception can sometimes suppress periods, but may also cause irregular bleeding. A prescribed progestogen course for bleeding is not automatically a contraceptive regimen. Confirm both its purpose and whether you need separate pregnancy prevention with the clinician.
For the broader choice when you also want contraception, our India contraceptive-method comparison covers daily use, bleeding patterns and fertility return. It should supplement, not replace, assessment of the current bleeding.
Hormonal IUS, including Mirena
An LNG-IUS releases a progestogen inside the womb and can substantially reduce bleeding while providing reversible contraception. NICE NG88 recommendation 1.5.2 recommends considering it first when there is no identified pathology, fibroids smaller than 3 cm that do not distort the cavity, or suspected/diagnosed adenomyosis. This is a selected group, not everyone with heavy bleeding.
A 2022 Cochrane overview by Bofill Rodriguez and colleagues (PMID 35638592) ranked LNG-IUS highest among first-line options for reducing menstrual blood loss. However, certainty was low for that outcome, and evidence about perceived improvement and satisfaction was very uncertain. A ranking does not guarantee a particular percentage reduction for you or mean tablets must fail first.
Insertion requires an examination and a trained local provider. Pain relief should be discussed beforehand. Spotting or irregular bleeding can occur initially; NICE advises allowing at least six cycles to assess benefit, not enduring severe bleeding or pain without review.
Hormone reaches the bloodstream as well as acting locally, so hormonal side effects are possible. Bayer’s prescribing information lists pregnancy, current pelvic infection, cavity-distorting uterine abnormalities, and known or suspected breast cancer or another progestin-sensitive cancer, current or past, among its contraindications. It also describes expulsion and perforation risks. It is a US document: the inserting clinician should confirm the current Indian product and indication-specific replacement instructions.
Our Mirena and heavy-periods guide explains selection, early bleeding, risks and the comparison with hysterectomy. Copper-T is different: it can make periods heavier and is not a treatment for heavy bleeding. If that is your current method, our copper-IUD period-change guide explains what to discuss with the inserting service.
Fibroid medicines and targeted procedures
For larger fibroids, cavity-distorting growths or persistent symptoms, discuss specialist treatment rather than repeatedly changing tablets without reassessment. NICE recommends considering specialist referral for fibroids 3 cm or larger; size, number, location and fertility plans all affect the options.
- Hysteroscopic treatment may remove a polyp or a fibroid projecting into the cavity. It can address that cause of bleeding, but is still a procedure with risks and no guarantee against recurrence.
- Myomectomy removes fibroids while retaining the uterus. It may preserve the possibility of pregnancy, but does not guarantee fertility or prevent new fibroids.
- Uterine artery embolisation (UAE) reduces the blood supply to fibroids. Keeping the uterus does not make its implications for a future pregnancy identical to myomectomy; discuss fertility outcomes before choosing.
- GnRH medicines can help control fibroid symptoms in selected circumstances, including preparation for surgery. Their duration, side effects and any accompanying hormone treatment require specialist supervision. Product availability and approved use in India must be checked locally.
These options are described in NICE NG88 sections 1.4–1.5 and ACOG’s abnormal-bleeding guidance. Other specialist techniques may be available for particular fibroids; this overview is not a list of every locally available device or medicine. A bleeding disorder or abnormal lining sample may require a different, cause-specific treatment plan.
Endometrial ablation
Ablation treats the womb lining to reduce bleeding. It is for selected women who do not want a future pregnancy, after assessment of the cavity and lining. Bleeding can return and further treatment may be needed, as described in Royal United Hospitals Bath’s ablation information. Lighter periods or no periods cannot be promised.
Ablation is not contraception. Pregnancy can still occur afterwards and can be dangerous, so effective contraception remains necessary. NICE and ACOG emphasise this. Keeping the uterus after ablation does not mean preserving the ability to safely carry a pregnancy.
Hysterectomy
Hysterectomy removes the uterus and provides definitive treatment for uterine bleeding, but permanently ends the ability to carry a pregnancy. It involves operative risks and recovery. Removing the ovaries is a separate decision, not an automatic part of every hysterectomy.
It can be appropriate when symptoms are severe, alternatives are unsuitable or unsuccessful, or a woman makes an informed choice after discussing options. NICE NG88 supports specialist referral when medicines are declined as well as when they fail. You do not need to try every medicine or device to have your preference taken seriously. Surgery is not evidence that you or your doctor failed.
How to choose, and what to ask this week
Bring whatever bleeding information you already have; do not delay assessment to collect two more cycles. Useful details are bleeding dates, flooding, pad/cup changes, pain, fatigue, medicines and any chance of pregnancy.
Ask your clinician:
- What is the likely cause, and do any symptoms need prompt investigation?
- Which tests will change my treatment, including a blood count and assessment of iron stores?
- Which options fit my pregnancy plans, and which provide contraception?
- What improvement should we expect, when will we review it, and when should I seek help sooner?
- If I decline an option or it does not help, what else can we consider?
For costs in India, request an itemised local estimate covering indicated tests, medicines or device, procedure, pain relief, follow-up and removal where relevant. This guide does not quote a national IUS-versus-hysterectomy package price; ask each service what its estimate includes. Cost matters, but the two treatments are not interchangeable simply because one quote is lower.
For a non-urgent discussion of your reports and choices, send Dr. Suganya a message on WhatsApp. Fertilia consultations are online, pan-India, alongside care from your local gynaecologist. Heavy bleeding with faintness, breathlessness or severe symptoms needs local assessment, not a wait for our reply.
Frequently Asked Questions
How heavy is heavy enough to ask for help?
Bleeding that disrupts sleep, work, travel or ordinary activities is worth discussing. Frequent product changes, flooding, large clots or a period longer than seven days can help describe it. You do not have to measure 80 ml or meet several criteria.
Do I need ultrasound, ferritin and thyroid tests together?
There is no universal bundle. A full blood count is recommended; discuss iron-store testing too. NICE removed its advice against routine ferritin testing in July 2026. Thyroid tests depend on other thyroid symptoms, while ultrasound or hysteroscopy depends on the suspected cause.
Which treatment works best?
An LNG-IUS often provides strong bleeding reduction for suitable women. Tablets, targeted procedures, ablation and hysterectomy have different benefits and limitations. The cause, symptoms, fertility plans and your preferences matter more than an across-the-board percentage ranking.
Can I avoid surgery?
Many women can use medicines or an IUS, but these do not suit or help everyone. A polyp, particular fibroid, severe symptoms or abnormal lining findings may change the plan. You can discuss alternatives without treating surgery as a bad outcome.
Can food alone correct the anaemia?
Food supports iron intake but does not replace prescribed iron treatment when needed. Treat the iron deficiency and the ongoing bleeding, with a follow-up plan for both.
Is ablation suitable if I may want a baby later?
No. It is not a fertility-preserving treatment. Pregnancy afterwards can be dangerous, and contraception is still needed because ablation itself does not prevent pregnancy.
Does a normal ultrasound mean nothing is wrong?
No. Some causes are not structural, and ultrasound cannot exclude every cavity or lining problem. Persistent symptoms may require a different investigation or treatment even when the scan is reassuring.
This is general information, not a personal prescription. Bring new, persistent or changing bleeding to a clinician’s attention, even if a previous test was normal.



